free counters
‏إظهار الرسائل ذات التسميات Forensic. إظهار كافة الرسائل

الجمعة، 14 أغسطس 2009

Forensic Science


Forensic Science
Salem Press | 2008-10-17 | ISBN : 1587654239 | Pages: 1056 | PDF | 17.33 MB


Download Link


الأربعاء، 12 أغسطس 2009

Incest


Incest refers to any sexual activity between closely related persons (often within the immediate family) that is illegal or socially taboo. The type of sexual activity and the nature of the relationship between persons that constitutes a breach of law or social taboo vary with culture and jurisdiction. Some societies consider it to include only those who live in the same household, or who belong to the same clan or lineage; other societies consider it to include "blood relatives"; other societies further include those related by adoption or marriage.[1]

According to some studies,[2] the most frequently reported type of incest is father-daughter incest. However, others studies[3][4][5] suggest that sibling incest occurs as often, or more often, than other types of incest. Incest between adults and prepubescent or adolescent children is considered a form of child sexual abuse[6][7] that has been shown to be one of the most extreme forms of childhood trauma, a trauma that often does serious and long-term psychological damage, especially in the case of parental incest.[8] Prevalence is difficult to generalize, but research has estimated 10-15% of the general population as having at least one incest experience, with less than 2% involving intercourse or attempted intercourse.[9] Among women, research has yielded estimates as high as twenty percent.[8]

Consensual adult incest is rarely reported.[citation needed] Consensual incest between adults is criminalized in most countries,[10] although it is seen by some as a victimless crime.[11][12]

Most societies have some form of incest avoidance.[13][14] The incest taboo is and has been one of the most common of all cultural taboos, both in current nations and many past societies,[15] with legal penalties imposed in some jurisdictions. Most modern societies have legal or social restrictions on closely consanguineous marriages.[16] However, in some societies, such as that of Ancient Egypt, brother–sister, father–daughter, and mother–son relations were practiced among royalty.[17][18] In addition, the Balinese[19] and some Inuit tribes[20] have altogether different beliefs about what constitutes illegal and immoral incest.

الأربعاء، 5 أغسطس 2009

Forensic Psychology: Emerging Topics and Expanding Roles

هذا الكتاب يناقش مجال علم النفس من زاويه الطب الشرعى
Forensic Psychology: Emerging Topics and Expanding Roles, كتاب طبى
                                        
                                                                                                 download link
                           

الأربعاء، 22 يوليو 2009

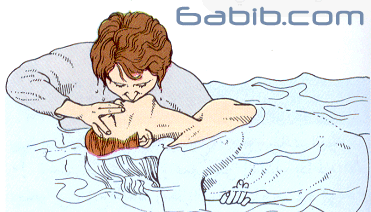
الغرق Drowning


 الغرق يؤدى إلى الاختناق عن طريق دخول الماء إلى الرئتين أو بتشنج الحنجرة و الذي ينجم عنه ضيق المسالك التنفسية( الغرق الجاف ).
                 ولا تضيع وقتك في محاولة إخراج الماء من رئتي المصاب .

قد يحدث احتقان الرئتين بسرعة pulm. edema ، ولكن ربما مرت عدة ساعات قبل أن يظهر ، لذلك يجب إرسال جميع الغرقى الذين تم      إنقاذهم إلى المستشفى  للعلاج
  وإذا حصل الغرق في ماء بارد فقد يتعرض المصاب لخطر هبوط درجة الحرارة ، لذلك كان من الأهمية بمكان تدفئته
الأعراض و العلامات :

- نفس أعراض وعلامات الاختناق
- ظهور الزّبد حول شفتي المصاب وفمه وأنفه
الغرض من العلاج:
إدخال الهواء إلى رئتي المصاب بأسرع ما يمكن ، حتى في الماء إذا لزم الأمر ، والعمل على نقله إلى المستشفى .
العلاج:
 أخرج من فم المصاب بسرعة كل ما يمكن أن يسد المسالك كالأعشاب البحرية ، وابدأ التنفس الصناعي فوراً . حتى في الماء يمكن بدء التنفس الصناعي إذا كان المصاب ساكناً
وإذا كان عمق الماء يمكّنك ، استعمل إحدى يديك لسند جسم المصاب واليد الأخرى لسند رأسه وسدّ أنفه وقم بإجراء التنفس من الفم للفم
وإذا حصل الغرق في مياه عميقة ، قم بالنفخ عندما تتمكن أثناء سحب المصاب إلى الشاطيء

- عندما تتمكن من وضعه على سطح صلب ، تحقق من تنفسه ونبضه ، وواصل الانعاش إذا لزم الأمر
- بمجرد أن يبدأ المصاب بالتنفس ، ضعه في وضع الافاقة
- قم بتدفئته ، وإذا أمكن انزع عنه الملابس المبللة وجففه ، وتغطيتة، وعند الضرورة عالج هبوط الحرارة
- اعمل على نقله إلى المستشفى  فى اسرع وقت


الأحد، 19 يوليو 2009

Forensic psychology, a branch of interest

Forensic psychology is the intersection between psychology and the criminal justice system. It involves understanding criminal law in the relevant jurisdictions in order to be able to interact appropriately with judges, attorneys and other legal professionals. An important aspect of forensic psychology is the ability to testify in court, reformulating psychological findings into the legal language of the courtroom, providing information to legal personnel in a way that can be understood.[1] Further, in order to be a credible witness, for example in the United States, the forensic psychologist must understand the philosophy, rules and standards of the American judicial system. Primary is an understanding of the adversarial model under which the system functions. There are also rules about hearsay evidence and importantly the exclusionary rule. Lack of a firm grasp of these procedures will result in the forensic psychologist losing credibility in the courtroom.[2] A forensic psychologist can be trained in clinical, social, organizational or any other branch of psychology.[3] In the United States, the salient issue is the designation by the court as an expert witness by training, experience or both by the judge. Generally, a forensic psychologist is designated as an expert in a particular jurisdiction. The number of jurisdictions in which a forensic psychologist qualifies as an expert increases with experience and reputation.

Questions asked by the court of a forensic psychologist are generally not questions regarding psychology but are legal questions and the response must be in language the court understands. For example, a forensic psychologist is frequently appointed by the court to assess a defendant's competency to stand trial

الأربعاء، 8 يوليو 2009

Forensic Entomology Book


Forensic Entomology: An Introduction By Dorothy Gennard 
Publisher: Wiley | ISBN: 0470014792 | edition 2007 | PDF | 244 pages | 4,8 mb

Download Link

http://depositfiles.com/en/files/1w5xfm59b

الخميس، 2 يوليو 2009

Sexual Assault


Sexual Assault: What to Do

If you have been sexually assaulted or think you have been, first, you must overcome the stigma of reporting the event. The stigma of reporting a sexual assault or rape for both women and men is not as great as it once was, and this change works in favor of the victim. The women's movement and the media have done a great deal to remove the stigma of being a victim of sexual assault. 

If sexual assault has taken place, you should report the crime for many important reasons, including the following: 

To keep the same person from assaulting others 


To provide psychological closure for you 


To be certain about your own health and have an examination to rule out medical problems related to the assault

Sexual assault is an emotionally charged crime in which passions for prevention and prosecution run at a high level. Many people involved in sexual assault work have been victims of sexual assault themselves. These people take on the role of advocates and support persons for victims of sexual assault. Special sexual assault examination centers have been set up in most cities to work with victims of sexual assault in a sensitive manner. 


Report sexual assault to law enforcement as soon as possible. Although you may have many reasons for delay (such as fear, guilt, and confusion), any delay in reporting can and will be regarded as suspect and inevitably used to imply that you are making a false allegation. 


Tell family and friends immediately, and inform law enforcement at the same time. Family and friends can be helpful during the most difficult early moments after an assault. 


Use these steps in reporting sexual assault: 

When reporting sexual assault, document as many details as possible, as soon as possible. Accurate recall of events will fade quickly, and documentation in sufficient detail soon after an incident is thought of as more reliable evidence in the legal proceedings that will follow. 


Note the location and time of any events. Describe the number and characteristics of the assailant or assailants. Write down as much detail as possible about the circumstances surrounding the assault as soon as possible after the assault. Make an effort to recall each and every aspect of what occurred during the assault and turn over this information to law enforcement. Each of these details increases the chances that the suspect will be caught and successfully prosecuted: 

Each activity 


The sequence of activities 


How long each activity lasted 


What was said and by whom 


The number of times that resistance was offered 


The type of resistance 


Any unusual details 


Any associated physical assault 


Any pain 


Types of threats that were used 


Whether weapons were talked about, used, or seen during the assault 


Any bodily fluids seen or felt 


Any injuries that may have been inflicted on the assailant 


Maintain as much evidence as possible in its intact state. Do not wipe away or throw away any secretions that can be identified. Do not wash or change clothing, bedding, furniture, or any fabric. Put these items into dry paper bags and seal them. 


Resist the strong urge to clean up by washing, showering, and douching. You will be given a special sexual assault examination by trained health professionals at a hospital, and specimens that will be collected are very important in proving the guilt of the assailant. Many of these specimens contain DNA evidence that can provide conclusive proof of the identity of the assailant.

الجمعة، 26 يونيو 2009

Autopsy


An autopsy is a medical procedure that consists of a thorough examination performed on a body after death, to evaluate disease or injury that may be present and to determine the cause and manner of a person's death.

The decision about an autopsy occurs at a difficult time for most families since they have just lost a loved one. Counselors or spiritual advisors who specialize in bereavement services may be available to help families through the process. Family members may consider an autopsy:
When a medical condition has not been previously diagnosed.
If there are questions about an unexpected death that appears due to natural causes.
If there are genetic diseases or conditions that they also may be at risk for developing.
When the death occurs unexpectedly during medical, dental, surgical, or obstetric procedures.
When the cause of death could affect legal matters.
When the death occurs during experimental treatment.
An autopsy may be required in deaths that have medical and legal issues and that must be investigated by the medical examiner's or coroner's office, the governmental office that is responsible for investigating deaths that are important to the public's health and welfare. Deaths that must be reported to and investigated by the medical examiner's or coroner's office can vary by state and may include those that have occurred:
Suddenly or unexpectedly, including the sudden death of a child or adult, or the death of a person who was not under the care of a doctor at the time of death.
As a result of any type of injury, including a fall, motor vehicle accident (MVA), drug overdose, or poisoning.
Under suspicious circumstances, such as a suicide or murder.
Under other circumstances defined by law.

In some of these deaths an autopsy may be required, and the coroner or medical examiner has the legal authority to order an autopsy without the consent of the deceased person's family (next of kin). If an autopsy is not required by law, it cannot be performed unless the deceased person's family provides permission.

An autopsy is generally performed by a doctor (pathologist) who has training and expertise in the examination of body tissues and fluids.

Should I have an autopsy done on my loved one?
Why It Is Done

An autopsy is done to:
Determine as precisely as possible what caused the death. This can sometimes provide family members with information about diseases or conditions that they also may be at risk for developing.
Confirm or exclude a disease diagnosis made before death (such as Alzheimer's disease). An autopsy also may be done to help understand how a given disease progresses or to determine the effectiveness of the treatment for that disease.
Document the presence of a disease that was undiagnosed before death.
Collect samples of body fluids or tissues for possible genetic testing. This is generally done only after discussion with the deceased person's family.
Collect evidence and information in criminal cases.
Help health departments or other government agencies identify and track a disease or potential public health hazard (such as a suspected contagious disease or contaminated drinking water).

الجمعة، 19 يونيو 2009

What is DNA evidence?


Anything biological...
...blood, semen/sperm, hair,
...tissue, bones, organs, tooth pulp
...bodily secretions, saliva,
  ...sweat, urine, fingernails


DNA Evidence can be found virtually anywhere

- If it's biological, it's potential DNA evidence
- People constantly shed DNA
- There are 3,000,000,000,000 cells in the human body...only
about 100 are needed to obtain a DNA profile

There are two types of DNA testing used in criminal and non-criminal investigations:

Mitochondrial DNA:


1. Found in the cytoplasm of the cell
2. Runs along the maternal line  
- siblings share the same mitochondrial DNA
with their mother, grandmother, etc...
3. Can be found in hair shafts  
STR DNA

1. Found in the nucleus of the cell
2. PCR/STR DNA
3. Most commonly used in criminal
investigation casework

Uses of DNA in Criminal Investigations:

1. Identifying remains
2. Provides a Record of a particular person
being in a particular place
3. Ownership of personal items such as clothing
4. Determining Kinship

DNA collection

STR DNA technology changed the rules of evidence handling:
1. STR DNA increased sensitivity in testing
2. STR DNA increased awareness in evidence handling
  - As a result, the crime scene investigator must take great precautions to avoid
  the contamination of DNA evidence

In the past, all crime scenes needed to be protected against elements such as: Weather, Animals, 
and Traffic. With the inception of STR DNA testing, the crime scene investigator must also be 
concerned with scene contamination by crime scene personnel.

It is imperative that crime scene personnel take precautions to avoid contamination of DNA evidence:

1. Personal Protective Equipment (PPE) should be worn at all times.
- a single hair or drop of sweat from an unprotected person could leave an unknown DNA
 sample at the scene
2. When collecting DNA samples, the crime scene investigator should change gloves and forceps
after each item is collected, in order to avoid cross contamination between items of evidence
Documenting and Collecting DNA Samples:

1. Photograph stain/sample with and without a scale
2. Carefully swab the stain
  - preferably with no dilution
  - if stain is dry, use one drop of distilled water on the swab
3. Allow to air dry before packaging
4. Carefully label & seal (date, time, initials).
5. Maintain the chain of custody.
6. Provide information that you think may be important.
  - Note if items were collected from an unusual location or might  
  have possible contaminants.
7. Forward to the forensic lab ASAP

The proper collection and storage of biological evidence for DNA 
testing includes the following:

1. Biological evidence should be allowed to air dry before  
packaging.
  - ideally, it should be hung up in a clean dry room,
  away from direct sunlight
2. Biological evidence should be packaged in paper bags.
  - paper breaths, and allows the item of evidence to
  remain dry.
  - Plastic bags do not breath, and can cause moisture
  and mold to grow on the evidence, which in turn can
  have a negative affect on DNA testing
3. Biological evidence should be stored under laboratory
conditions as available resources permit - or in a
cool, dry climate, free of moisture
4. Place liquid items in collection tubes and refrigerate  

Before a DNA test can be performed, a control sample should be 
obtained from the victim, suspect, and any other persons whose DNA 
may be found on the item of evidence.

A control sample can be in the form of whole blood, a buccal swab, or 
any other known exemplar from the person in question. The easiest 
type of DNA control sample to obtain is a buccal swab. A buccal swab 
involves swabbing the inside of a person's cheek with an approved 
type of swab, for about 30 seconds, to secure the buccal cells that are 
found on the inside of the cheek. If done properly, a full DNA profile 
can be obtained from this swab.

–Before obtaining DNA control samples, consider having the person
in question sign a DNA consent form.  


DNA Collection:
RFLP (Restriction Fragment Length Polymorphism)
- this was the first type of DNA used in criminal investigations
- in order to run an RFLP test, a large biological sample was needed,
(usually at least the size of a quarter)
- this type of test usually provided a fairly discriminating result
- IE: a probability result of 1 in 1,000,000

PCR (Polymearse Chain Reaction) - first generation
- to run this type of test, a very small biological sample is needed, and that sample
can be amplified, or reproduced, to obtain a DNA profile
- the results are not as discriminating
- IE: a probability result of 1 in 25,000

STR (Short Tandem Repeat) second generation PCR
- This is the current form of DNA testing currently used in most forensic DNA labs.
STR testing provides the “best of both worlds”
- only a very small biological sample is required, (sometimes the sample is not even
visible to the naked eye.)
- STR DNA provides a very discriminating result
- IE: a probability result of 1 in 300,000,000,000

Age Determination

Although the actual age can not be determined by bones, the approximate age of the individual can be.

For age determination, different parts of the skeleton are more useful at different age ranges. The different age ranges include perinatal, neonate, infants and young children, late childhood, adolescence, young adult, and older adult.

The age of perinatals, those that are not yet born, can be determined by looking at bone size. This is because outside factors such as malnutrition on the mother's part is not going to affect the fetus' growth as much. During periods of low food intake the mother's body will give nutrients to the fetus, shorting the mother of nutrients.

Neonates, babies who have not gotten their teeth yet, are very difficult to accurately determine the age of because of individual variation of development. As a group, the neonates have no teeth, many areas of the skeleton have not fused together (especially the cranium and pelvis), and they have very small bones. 

Infants and young children will usually have some of their teeth in. The formation of teeth is often used in age determination for this group. Permanent teeth start to form at birth, thus the formation of permanent teeth is a relatively good age determinant. Some ossification has begun in the bones at this age, this means that soft parts of the bones become hard. However, this is not as good a determinant.

Late childhood is when the permanent teeth begin to come in. More bones begin to ossify.

Adolescence shows increased long bone length and fusion of the ends (or cap) to the shaft. This fusion is a particularly useful age technique. Each cap, or epiphysis, fuses to the shaft, or diaphysis, at a particular age range.

Young adults and older adults have several methods of age determination: closure of the cranial sutures; morphology of rib-ends, auricular surface and pubic symphysial; microstructure of bone and teeth; wear on teeth, incremental layers of cementum; and finally the 'Complex Method'. 

Cranial sutures (non-movable joints in the head) slowly fuse together, becoming obliterated in time. Although this has been known for many years, there has only been a weak association established between age and closure.

The morphology of rib-ends changes through age. Ribs are connected to the sternum by cartilage. The rib ends that meet with the cartilage are relatively flat at first, but during the aging process the ends become ragged and the cartilage becomes pitted. The irregularity of the rib ends has been found to relate to age at death.

الأربعاء، 18 مارس 2009

Abdominal Trauma, Blunt

The care of the trauma patient is demanding and requires speed and efficiency. Evaluating patients who have sustained blunt abdominal trauma remains one of the most challenging and resource-intensive aspects of acute trauma care.

Missed intra-abdominal injuries and concealed hemorrhage are frequent causes of increased morbidity and mortality, especially in patients who survive the initial phase after an injury.

Physical examination findings are notoriously unreliable for several reasons; a few examples are the presence of distracting injuries, an altered mental state, and drug and alcohol intoxication in the patient.

Coordinating a trauma resuscitation demands a thorough understanding of the pathophysiology of trauma and shock, excellent clinical and diagnostic acumen, skill with complex procedures, compassion, and the ability to think rationally in a chaotic milieu.

Blunt abdominal trauma usually results from motor vehicle collisions, assaults, recreational accidents, or falls. The most commonly injured organs are the spleen, liver, retroperitoneum, small bowel, kidneys, bladder, colorectum, diaphragm, and pancreas. Men tend to be affected slightly more often than women.
Frequency


United States

By nearly every measure, injury ranks as one of this nation's most pressing health issues. More than 150,000 people die each year as a result of injuries, such as motor vehicle crashes, fires, falls, drowning, poisoning, suicide, and homicide. Injuries are the leading cause of death and disability for US children and young adults.

According to the 2000 statistics from the National Center for Injury Prevention and Control, trauma (unintentional and intentional) was the leading cause of death in persons aged 1-44 years. Further review of the data reveals that in those aged 15-25 years, 14,113 persons died from unintentional injuries, 73% of which were related to vehicular trauma. In individuals aged 25-34 years, 57% of the 11,769 deaths reported were from motor vehicle collisions.

In 2001, approximately 30 million people visited emergency departments for the treatment of nonfatal injuries and more than 72,000 people were disabled by injuries. Injury imposes exceptional costs, both in health care dollars and in human losses, to society.

International

In 1990, approximately 5 million people died worldwide as a result of injury. The risk of death from injury varied strongly by region, age, and sex. Approximately 2 male deaths due to violence were reported for every female death. Injuries accounted for approximately 12.5% of all male deaths, compared with 7.4% of female deaths.

Globally, injury accounts for 10% of all deaths; however, injuries in sub-Saharan Africa are far more destructive than in other areas. In sub-Saharan Africa, the risk of death from trauma is highest in those aged 15-60 years, and the proportion of such deaths from trauma is higher than in any other region of the world. In South Africa, for instance, the traffic death rate per unit of distance traveled is only surpassed by Korea, Kenya, and Morocco.

Estimates indicate that by 2020, 8.4 million people will die yearly from injury, and injuries from traffic collisions will be the third most common cause of disability worldwide and the second most common cause in the developing world.
Pathophysiology

Vehicular trauma is by far the leading cause of blunt abdominal trauma in the civilian population. Auto-to-auto and auto-to-pedestrian collisions have been cited as causes in 50-75% of cases. Rare causes of blunt abdominal injuries include iatrogenic trauma during cardiopulmonary resuscitation, manual thrusts to clear an airway, and the Heimlich maneuver.

Intra-abdominal injuries secondary to blunt force are attributed to collisions between the injured person and the external environment and to acceleration or deceleration forces acting on the person's internal organs. Blunt force injuries to the abdomen can generally be explained by 3 mechanisms.

The first is when rapid deceleration causes differential movement among adjacent structures. As a result, shear forces are created and cause hollow, solid, visceral organs and vascular pedicles to tear, especially at relatively fixed points of attachment. For example, the distal aorta is attached to the thoracic spine and decelerates much more quickly than the relatively mobile aortic arch. As a result, shear forces in the aorta may cause it to rupture. Similar situations can occur at the renal pedicles and at the cervicothoracic junction of the spinal cord.

The second is when intra-abdominal contents are crushed between the anterior abdominal wall and the vertebral column or posterior thoracic cage. This produces a crushing effect, to which solid viscera (eg, spleen, liver, kidneys) are especially vulnerable.

The third is external compression forces that result in a sudden and dramatic rise in intra-abdominal pressure and culminate in rupture of a hollow viscous organ (ie, in accordance with the principles of Boyle law).
Presentation

History

The initial assessment of a trauma patient begins at the scene of the injury, with information provided by the patient, family, bystanders, or paramedics. Important factors relevant to the care of a patient with blunt abdominal trauma, specifically those involving motor vehicles, include the following:
The extent of vehicular damage
Whether prolonged extrication was required
Whether the passenger space was intruded
Whether a passenger died
Whether the person was ejected from the vehicle
The role of safety devices such as seat belts and airbags
The presence of alcohol or drug use
The presence of a head or spinal cord injury
Whether psychiatric problems were evident

Priorities in resuscitation and diagnosis are established based on hemodynamic stability and the degree of injury. The goal of the primary survey, as directed by the Advanced Trauma Life Support protocol, is to identify and expediently treat life-threatening injuries. The protocol includes the following:
Airway, with cervical spine precautions
Breathing
Circulation
Disability
Exposure

Key elements of the pertinent history include the following:
Allergies
Medications
Past medical and surgical history
Time of last meal
Immunization status
Events leading to the incident
Social history, including history of substance abuse
Information from family and friends

Resuscitation is performed concomitantly and continues as the physical examination is completed. The secondary survey is the identification of all injuries via a head-to-toe examination.

It is imperative for all personnel involved in the direct care of a trauma patient to exercise universal precautions against body fluid exposure. The incidence of infectious diseases (eg, HIV, hepatitis) is significantly higher in trauma patients than in the general public, with some centers reporting rates as high as 19%. Even in medical centers with relatively low rates of communicable diseases, safely determining who is infected with such pathogens is impossible. The standard barrier precautions include a hat, eye shield, face mask, gown, gloves, and shoe covers. Unannounced trauma arrival is probably the most common situation that leads to a breach in barrier precautions. Personnel must be instructed to adhere to these guidelines at all times, even if it means a 30-second delay in patient care.
Physical examination

The evaluation of a patient with blunt abdominal trauma must be accomplished with the entire patient in mind, with all injuries prioritized accordingly. This implies that injuries involving the head, the respiratory system, or the cardiovascular system may take precedence over an abdominal injury.

The abdomen should neither be ignored nor the sole focus of the treating clinician and surgeon. In an unstable patient, the question of abdominal involvement must be expediently addressed. This is accomplished by identifying free intra-abdominal fluid using diagnostic peritoneal lavage (DPL) or the Focused Assessment with Sonography for Trauma (FAST) examination. The objective is to rapidly identify patients who need a laparotomy.

The initial clinical assessment of patients with blunt abdominal trauma is often difficult and notably inaccurate. Associated injuries often cause tenderness and spasms in the abdominal wall and make diagnosis difficult. Lower rib fractures, pelvic fractures, and abdominal wall contusions may mimic the signs of peritonitis. In a collected series of 955 patients, Powell et al reported that clinical evaluation alone has an accuracy rate of only 65% for detecting the presence or absence of intraperitoneal blood.1 In general, accuracy increases if the patient is examined repeatedly and at frequent intervals. However, repeated examinations may not be feasible in patients who need general anesthesia and surgery for other injuries. The greatest compromise of the physical examination occurs in the setting of neurologic dysfunction, which may be caused by head injury or substance abuse.

The most reliable signs and symptoms in alert patients are pain, tenderness, gastrointestinal hemorrhage, hypovolemia, and evidence of peritoneal irritation. However, large amounts of blood can accumulate in the peritoneal and pelvic cavities without any significant or early changes in the physical examination findings.

The abdominal examination must be systematic. The abdomen is inspected for abrasions or ecchymosis. The seat belt sign, ie, a contusion or abrasion across the lower abdomen, is highly correlated with intraperitoneal pathology. Visual inspection for abdominal distention, which may be due to pneumoperitoneum, gastric dilatation, or ileus produced by peritoneal irritation, is important. Ecchymosis involving the flanks (Grey Turner sign) or the umbilicus (Cullen sign) indicates retroperitoneal hemorrhage, but this is usually delayed for several hours to days. Rib fractures involving the lower chest may be associated with splenic or liver injuries. Auscultation of bowel sounds in the thorax may indicate the presence of a diaphragmatic injury. Palpation may reveal local or generalized tenderness, guarding, rigidity, or rebound tenderness, which suggests peritoneal injury.

A rectal examination should be performed to search for evidence of bony penetration resulting from a pelvic fracture, and the stool should be evaluated for gross or occult blood. The evaluation of rectal tone is important for determining the patient's neurologic status, and palpation of a high-riding prostate suggests urethral injury.

A nasogastric tube should be placed routinely (in the absence of contraindications, eg, basilar skull fracture) to decompress the stomach and to assess for the presence of blood. If the patient has evidence of a maxillofacial injury, an orogastric tube is preferred.

As the assessment continues, a Foley catheter is placed and a sample of urine is sent for analysis for microscopic hematuria. If injury to the urethra or bladder is suggested because of an associated pelvic fracture, then a retrograde urethrogram is performed before catheterization.

Because of the wide spectrum of injuries, frequent reevaluation is an essential component in the management of patients with blunt abdominal trauma.

Pediatric patients are assessed and treated at least initially as adults with respect to the primary and secondary surveys. However, obvious anatomical and clinical differences exist and these must be kept in mind: the child's physiologic response to injury is different; communication is not always possible; physical examination findings become more important; the pediatric patient's blood volume is less, predisposing them to rapid exsanguination; technical procedures tend to be more time consuming and challenging; and a child's relatively large body surface area contributes to rapid heat loss. Perhaps, the most significant difference between pediatric and adult blunt trauma is that, for the most part, pediatric patients can be resuscitated and treated nonoperatively. Some pediatric surgeons often transfuse up to 40 mL/kg of blood products in an effort to stabilize a pediatric patient. Obviously, if this fails and the child continues to be unstable, laparotomy is indicated.

Tertiary examination

This concept was first introduced by Enderson et al to assist in the diagnosis of any injuries that may have been missed during the primary and secondary surveys.2 The tertiary survey involves a repetition of the primary and secondary surveys and a revision of all laboratory and radiographic studies. In one study, a tertiary trauma survey detected 56% of injuries missed during the initial assessment within 24 hours of admission.
Indications

Aggressive radiographic and surgical investigation is indicated in patients with persistent hyperamylasemia or hyperlipasemia, conditions that suggest significant intra-abdominal injury.

Stable patients with inconclusive physical examination findings should undergo radiographic studies of the abdomen.

DPL is indicated in blunt trauma as follows:
Patients with a spinal cord injury
Those with multiple injuries and unexplained shock
Obtunded patients with a possible abdominal injury
Intoxicated patients in whom abdominal injury is suggested
Patients with potential intra-abdominal injury who will undergo prolonged anesthesia for another procedure

An indication for immediate blood transfusion is hemodynamic instability despite the administration of 2 L of fluid to adult patients; this instability indicates ongoing blood loss.

Indications for laparotomy in a patient with blunt abdominal injury include the following:
Signs of peritonitis
Uncontrolled shock or hemorrhage
Clinical deterioration during observation
Hemoperitoneum findings after FAST or DPL examinations

Finally, surgical intervention is indicated in patients with evidence of peritonitis based on physical examination findings.
Relevant Anatomy

The abdomen can be arbitrarily divided into 4 areas.

The first is the intrathoracic abdomen, which is the portion of the upper abdomen that lies beneath the rib cage. Its contents include the diaphragm, liver, spleen, and stomach. The rib cage makes this area inaccessible for palpation and complete examination.

The second is the pelvic abdomen, which is defined by the bony pelvis. Its contents include the urinary bladder, urethra, rectum, small intestine, and, in females, the ovaries, fallopian tubes, and uterus. Injury to these structures may be extraperitoneal in nature and therefore difficult to diagnose.

The third is the retroperitoneal abdomen, which contains the kidneys, ureters, pancreas, aorta, and vena cava. Injuries to these structures are very difficult to diagnose based on physical examination findings. Evaluation of the structures in this region may require a CT scan, angiography, and an intravenous pyelogram.

The fourth is the true abdomen, which contains the small and large intestines, the uterus (if gravid), and the bladder (when distended). Perforation of these organs is associated with significant physical findings and usually manifests with pain and tenderness from peritonitis. Plain x-ray films are helpful if free air is present. Additionally, DPL is a useful adjunct.
Contraindications

While not a contraindication to surgical repair, the evaluation of a patient with blunt abdominal trauma must be prioritized based on the most urgent problems. This implies that injuries involving the head, the respiratory system, or the cardiovascular system may take precedence over an abdominal injury.

Although a nasogastric tube is routine in order to decompress the stomach and assess for the presence of blood, it is contraindicated in patients with basilar skull fracture. An orogastric tube is preferred if the patient has evidence of a maxillofacial injury.

Operative treatment is not indicated in every patient with positive FAST scan results. Hemodynamically stable patients with positive FAST findings may require a CT scan to better define the nature and extent of their injuries. Operating on every patient with positive FAST scan findings may result in an unacceptably high laparotomy rate.

The only absolute contraindication to DPL is the obvious need for laparotomy. Relative contraindications include morbid obesity, a history of multiple abdominal surgeries, and pregnancy.

Resuscitative thoracotomy is not recommended in patients with blunt thoracoabdominal trauma who have pulseless electrical activity upon arrival in the emergency department. The survival rate in this situation is virtually 0%. These patients may be allowed a thoracotomy in the emergency department only if they have signs of life upon arrival to the emergency department.
source :emedicine